
Laminectomy: What Is It and Do You Really Need One?
A laminectomy is a spinal decompression surgery. It removes part of a vertebra called the lamina to make more space for compressed nerves. It is most often used for spinal stenosis when other treatments have not helped. A standing, weight-bearing scan can give your surgeon a clearer picture of how your spine behaves under load before surgery is decided.
Key points
- A laminectomy removes a small section of bone to relieve pressure on spinal nerves.
- It is usually considered after physiotherapy, injections or medicines have not worked.
- Lying-down scans can miss alignment problems that only appear when you stand and bear weight.
- An EOS standing scan shows your full spinal alignment with about 90% less radiation than a standard X-ray.
- ScanAlign provides diagnostic imaging only, not surgery or treatment.
What is a laminectomy?
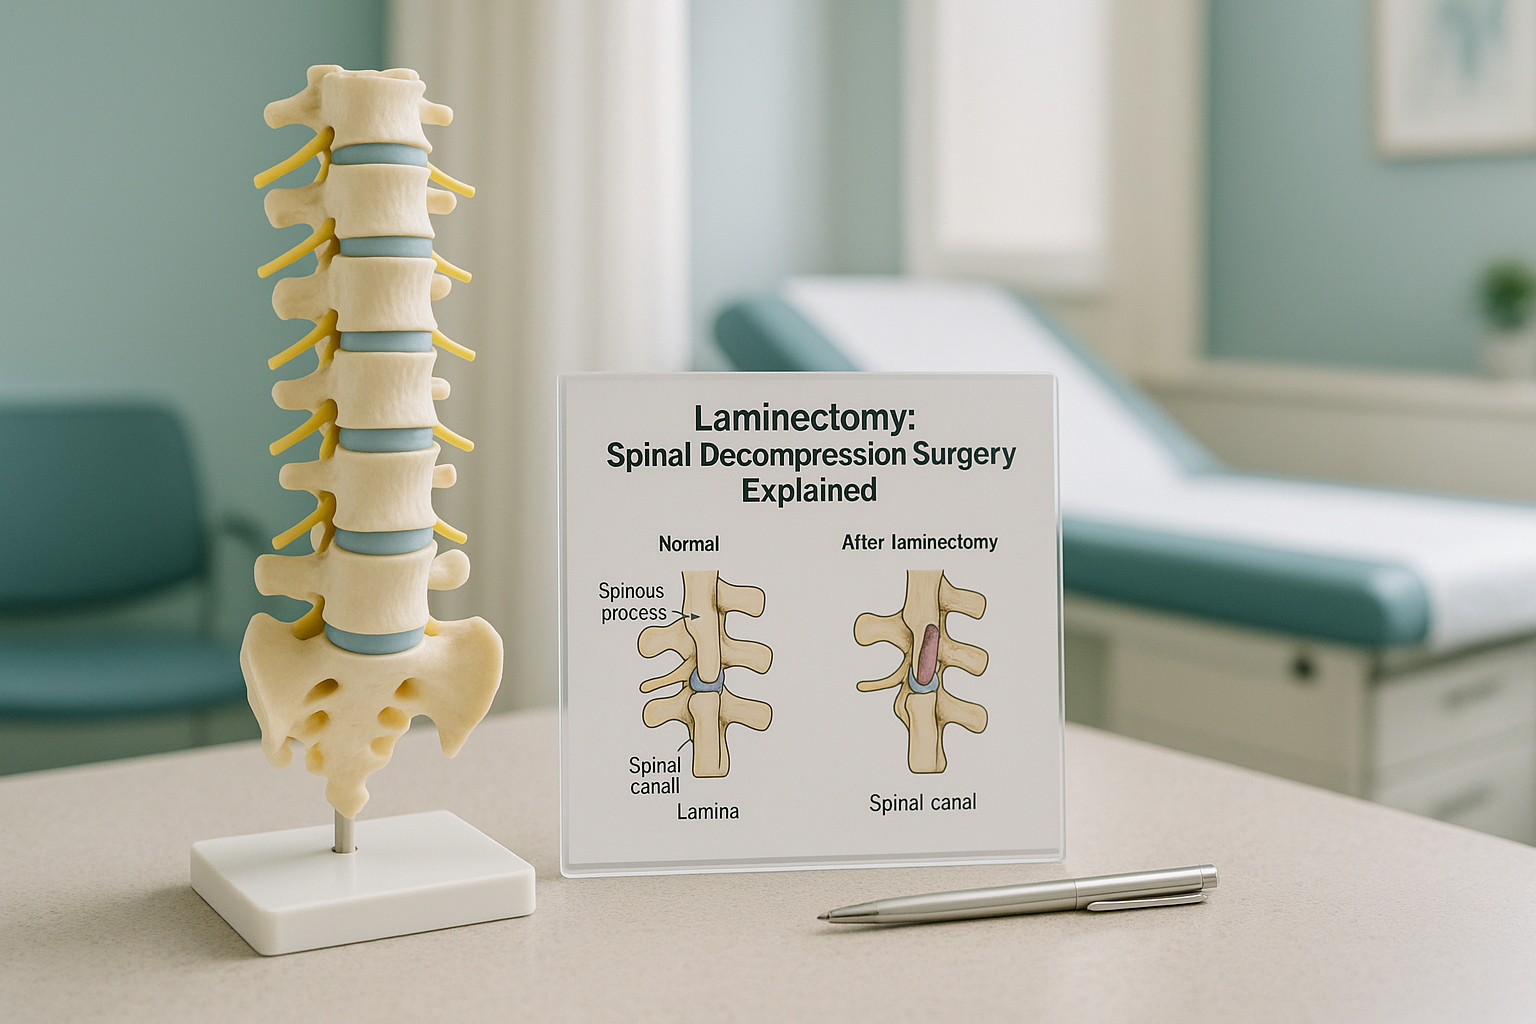
A laminectomy is an operation that removes part or all of the lamina, the bony arch at the back of a vertebra. This takes pressure off the spinal cord or nerve roots. The aim is to give the nerves more room so they stop being squeezed.
Most laminectomies are done on the lower (lumbar) spine, but they can also be done in the neck (cervical) area. Your surgeon may also trim thickened ligaments or remove bone spurs at the same time. In some cases, a spinal fusion is done along with the laminectomy to keep the spine stable afterwards.
Laminectomy vs laminoplasty
A laminoplasty is a slightly different method. Instead of removing the lamina fully, the surgeon hinges it open like a door and holds it in place with small spacers. This is more common in cervical (neck) surgery. It aims to keep some of the spine's natural structure. Your consultant will recommend the method that best suits your anatomy and condition.
What are the signs you might need a laminectomy?
A laminectomy is usually considered when spinal stenosis or another cause of nerve compression causes symptoms that have not improved with conservative treatment. Common signs include the following.
Leg or back pain that gets worse when you walk or stand for any length of time.
Pins and needles or loss of feeling in your legs, buttocks or feet.
Difficulty lifting your foot or climbing stairs, or a feeling that your legs may give way.
Having to stop and sit or lean forward often because your legs feel heavy or painful.
Urgent warning: If you have sudden loss of bladder or bowel control, severe or quickly worsening weakness in your legs, or numbness around your groin, get urgent medical help straight away. Contact your doctor or go to your nearest emergency department. These could be signs of cauda equina syndrome, which needs emergency treatment.
What conditions lead to a laminectomy?
The most common reason for a laminectomy is spinal stenosis, a narrowing of the spinal canal that puts pressure on the nerves. But it is not the only cause.
Gradual narrowing of the canal, often due to age-related changes in bone and ligament.
A bulging disc pressing on the nerve root, sometimes dealt with along with the laminectomy.
Bony overgrowths from arthritis that push into the space around the nerves.
Ligaments in the spinal canal that become thicker over time and crowd the nerves.
How does a standing scan help before a laminectomy?
A standing, weight-bearing scan shows your spine the way it actually works: under the force of gravity, with your muscles working. This matters because lying-down scans relax the body and can hide problems that only appear when you are upright.
Your body is a connected chain from your feet to your head. A tilt in the pelvis, a curve in the lower back or a shift in the hips can all change how forces travel through the spine. Pain often shows up away from its real cause, because one area makes up for a problem somewhere else. Conventional X-rays, CT scans and MRI are all taken lying down. This removes gravity and lets the spine spread out. A narrowed canal that causes real trouble when you stand may look less severe when you are flat on your back.
An EOS scan takes a full-length, standing image of your spine, pelvis and legs in a single pass, with about 90% less radiation than a standard X-ray, around ten times less. The image captures the true alignment and loading of every segment. Your surgeon can see exactly where the narrowing is worst and how the rest of your spine compensates. This gives them better information for planning the operation.
When MRI is the better tool: EOS shows bones, joints and alignment clearly. For soft tissue such as discs, nerves and the spinal cord itself, MRI is usually the better choice. Many surgical teams use both: MRI for soft tissue detail and a standing EOS scan for the whole-spine alignment picture.
Wondering whether a standing alignment scan in London could give your surgeon more information before your laminectomy?
Book a free video consultationWhat should you expect after a laminectomy?
Recovery after a laminectomy differs from person to person. It depends on things such as how many spinal levels were decompressed, whether a fusion was done at the same time, and your general health. Your surgical team will give you a personal recovery plan.
In general, most people are up and walking within a day of surgery. You will usually be advised to avoid heavy lifting and twisting for several weeks. Physiotherapy usually plays an important part in rebuilding strength and flexibility. Some people notice their leg symptoms improve quickly, while numbness or tingling can take longer to settle. Your consultant is the best person to discuss realistic timescales with you.
Laminectomy risks
All surgery carries risks. Common ones for a laminectomy include infection, bleeding, nerve injury and spinal fluid leak. There is also a chance that symptoms do not fully improve, or that the spine becomes less stable at the operated level over time. Your surgeon will explain these risks for your own situation before you give consent.
Better imaging before surgery can help reduce surprises. When your surgeon can see the full picture of your spinal alignment under load, they can plan more precisely, choose the right levels to decompress and decide whether a fusion is needed. This is where a standing EOS scan adds value, alongside the MRI or CT you already have.
Before you start a treatment, or change the one you are on, it is worth getting a detailed diagnosis. Knowing whether the cause sits in your pelvis, your legs or your spine changes what will actually help.
Frequently asked questions about laminectomy
A laminectomy removes part of the bony lamina to relieve pressure in the spinal canal. A discectomy removes part of a damaged disc that is pressing on a nerve. Sometimes both are done in the same operation.
Recovery time varies. Most people are walking within a day and can return to light daily activities within a few weeks. Full recovery, including a return to more demanding activities, can take several months. Your surgical team will guide you.
A laminectomy is one type of spinal decompression surgery. Other types include laminotomy, where only a small window of bone is removed, and foraminotomy, which widens the opening where the nerve root leaves the spine. Your surgeon will recommend the most suitable method.
A laminectomy removes the lamina. A laminoplasty hinges it open and uses spacers to keep the canal wider without removing the bone fully. Laminoplasty is more often used in the cervical spine.
No. You can self-refer. Many people book after a free video consultation to discuss whether a standing alignment scan is right for their situation. You can also be referred by your doctor, physiotherapist or consultant.
An EOS scan uses about 90% less radiation than a standard X-ray, around ten times less. This makes it one of the lowest-dose skeletal imaging options available.
No. EOS and MRI do different things. EOS shows bones, joints and whole-body alignment while standing. MRI shows soft tissue, discs, nerves and the spinal cord. Most surgical teams use both for a complete picture.
Spinal stenosis symptoms are usually worse when standing and walking, because gravity compresses the already narrow canal. Lying-down scans remove that load from gravity. This may make the narrowing look less severe than it actually is when you are upright.
The price for patients travelling from abroad is confirmed during the free video consultation, and you can see what is included on our FAQs and cost page.
No. ScanAlign is a diagnostic imaging clinic. We provide standing EOS scans and detailed reports that you and your medical team can use to plan treatment. We do not carry out surgery, injections or any form of treatment.
See your spine the way your surgeon needs to
A standing EOS scan can show your full spinal alignment under load. This gives your surgical team the detail they need to plan precisely. Start with a free video consultation from home.
Book a free video consultationSources
- NHS. "Lumbar decompression surgery." nhs.uk. Available at: nhs.uk/conditions/lumbar-decompression-surgery
- American Academy of Orthopaedic Surgeons (AAOS). "Lumbar Spinal Stenosis." OrthoInfo. Available at: orthoinfo.aaos.org
- Illés T, Somoskeöy S. "The EOS imaging system and its uses in daily orthopaedic practice." International Orthopaedics. 2012;36(7):1405-1411.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.