
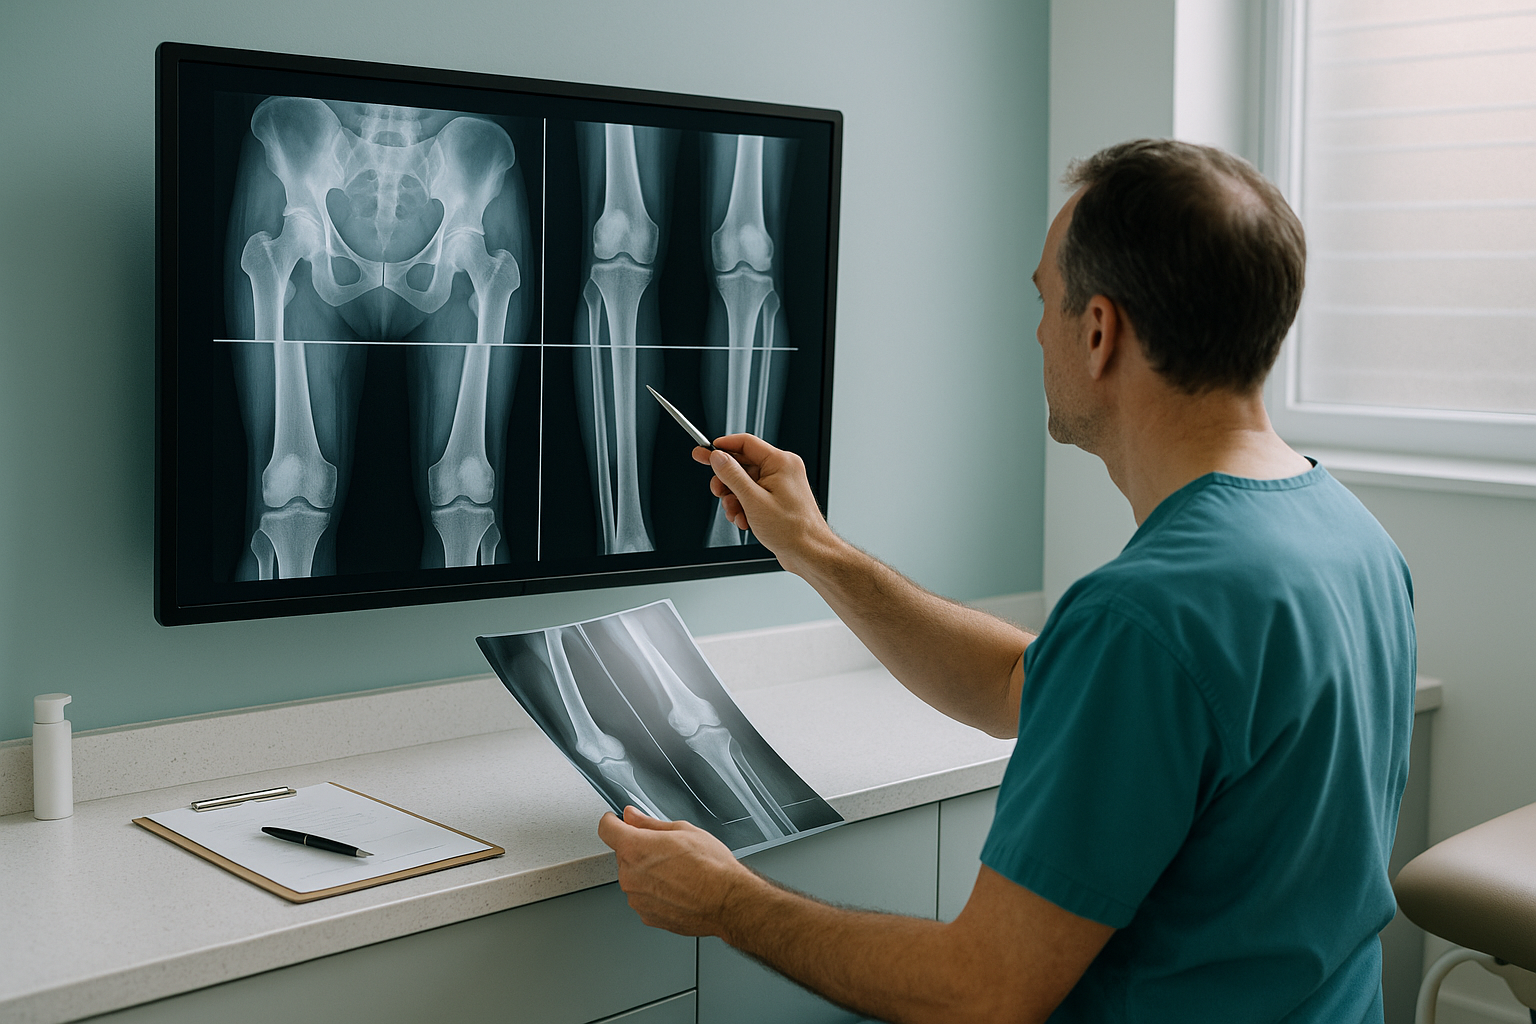
What Imaging Do Orthopaedic Surgeons Need for Pre-Operative Planning?
Imaging for pre-operative planning must show the full mechanical axis of both limbs under physiological load. Its measurements must be calibrated and accurate enough for implant templating. Standing, weight-bearing EOS imaging captures the whole lower limb, pelvis and spine in a single exposure. It has a built-in 1:1 scale and DICOM-ready output. This gives surgeons the data they need without magnification error.
Key points
- Standing EOS captures both limbs and the pelvis on one calibrated image, at 1:1 scale.
- Built-in calibration removes the magnification error linked with conventional radiographs.
- About 90% less radiation than a standard X-ray, around ten times less.
- Images are sent as DICOM files that work with your templating software.
- A fast referral pathway, from the moment you register to refer patients to delivery of the images.
Why does pre-operative imaging need to be weight-bearing?
In surgery, the only alignment that matters is alignment under load. When a patient lies down for a conventional radiograph, CT or MRI, gravity is taken away and the muscles relax. Joint spaces open, rotational deformities reduce and the mechanical axis shifts. The image may understate the very deformity you plan to correct.
Standing, weight-bearing imaging captures the skeleton in the position in which it actually works. Leg-length discrepancy, varus or valgus malalignment, pelvic obliquity and sagittal balance all show as they do in daily life. For pre-operative planning, this is the difference between templating on a best guess and templating on reality.
What does standing EOS imaging provide for surgical planning?
EOS gives a single, calibrated, full-length radiographic image of the patient standing upright. Both limbs, the pelvis and the spine are captured at the same time. The slot-scanning technology produces images at a true 1:1 ratio. So there is no magnification error and no need for an external calibration marker.
No magnification error. No ball marker needed. Measurements reflect true anatomy.
Images sent by DICOM transfer, ready for your templating software and PACS.
About 90% less radiation than a standard X-ray, around ten times less.
Full bilateral capture from hip to ankle. No stitching artefacts or alignment errors.
The result is an image you can template directly. You can be confident that the measurements for implant sizing, offset and component position reflect the patient's true standing anatomy.
How does EOS compare with conventional pre-operative imaging?
EOS addresses several well-documented limits of conventional radiography and CT for surgical planning. The table below sums up the key differences.
| Factor | Conventional X-ray | CT scanogram | Standing EOS |
|---|---|---|---|
| Patient position | Supine or standing (single region) | Supine | Standing, weight-bearing |
| Field of view | Single joint or stitched cassettes | Full leg, supine only | Both limbs, pelvis and spine in one exposure |
| Magnification | Variable, needs a calibration marker | Minimal | 1:1 scale, calibrated by design |
| Calibration marker needed | Yes | No | No |
| Radiation dose | Standard | Higher | About 90% less than a standard X-ray |
| Stitching artefacts | Possible with multiple cassettes | None | None |
| DICOM output | Usually | Yes | Yes |
A note on MRI. EOS shows bones, joints and alignment in excellent detail. For soft-tissue assessment, disc pathology or nerve compression, MRI is usually the better tool. Many surgical plans benefit from both.
How do I refer a patient for standing EOS imaging?
Referral is simple. You can register to refer patients through our online portal, or contact us directly at 19 Harley Street, London. No letter from the patient's family doctor is needed.
Register or refer
Fill in the short online form or send us the referral details directly. State the clinical question and which regions you need imaged.
Patient attends
Your patient travels to ScanAlign, standing EOS imaging in London at 19 Harley Street. The scan itself takes only a few seconds.
Calibrated images produced
Full-length, 1:1-scale images are produced with all relevant alignment measurements.
DICOM transfer
Images are sent to you by DICOM, ready to import into your PACS and templating software.
Ready to refer? Refer a patient for pre-operative imaging
Which surgical procedures benefit from standing EOS imaging?
Any procedure that depends on accurate limb alignment, leg-length measurement or implant sizing benefits from calibrated, weight-bearing imaging. Common reasons for referral include the following.
The low radiation dose also makes EOS well suited to post-operative follow-up imaging. Here, repeat scans may be needed over time to monitor component position or changes in alignment.
Before a patient starts treatment, or changes the one they are on, a detailed diagnosis is worth having. Knowing whether the cause sits in the pelvis, the legs or the spine changes what will actually help.
Frequently asked questions
No. You can refer directly as a consultant or surgeon. The patient can also refer themselves. No letter from the family doctor is needed.
EOS uses slot-scanning technology with a fixed, known geometry between the X-ray source and the detectors. This produces images at a true 1:1 ratio without the need for an external calibration marker. It removes the magnification error that conventional radiographs introduce.
Yes. Images are sent as standard DICOM files. They can be imported directly into your PACS and work with common templating software.
EOS delivers about 90% less radiation than a standard X-ray, around ten times less. This matters most when repeat imaging is needed for post-operative monitoring.
Yes. A single standing exposure captures both lower limbs from hip to ankle, along with the pelvis, on one continuous image. There is no need to stitch separate cassettes, so there are no stitching artefacts.
Yes. EOS is well suited to knee replacement planning because it shows the full mechanical axis under standing load. This allows accurate measurement of the HKA angle and confident templating of component sizes without magnification error. See our page on full-leg standing X-ray for more detail.
Yes. EOS captures the pelvis and spine in a standing position, so it shows functional pelvic tilt under load. This is valuable for planning acetabular component orientation, especially in patients with spino-pelvic imbalance.
The scan itself takes only a few seconds. The patient stands still inside the EOS system while the image is taken. The whole appointment is short.
Not always. EOS excels at showing bony alignment, joint spacing and mechanical axis under load. For soft-tissue detail, disc pathology or nerve assessment, MRI remains the better tool. For cross-sectional bone detail, CT has its own role. Many surgical plans use EOS alongside other modalities.
You can register to refer patients through our online referral portal, or contact us directly at 19 Harley Street, London.
Give your surgical plan the imaging it deserves
Standing, calibrated, 1:1-scale imaging sent by DICOM. Register to refer, or send us your first patient.
Refer a patient for pre-operative imagingWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Illés, T. & Somoskeöy, S. (2012). The EOS imaging system and its uses in daily orthopaedic practice. International Orthopaedics, 36(7), 1405-1411.
- Deschênes, S. et al. (2010). Diagnostic imaging of spinal deformities: reducing patients' radiation dose with a new slot-scanning X-ray imager. Spine, 35(9), 989-994.
- British Orthopaedic Association. Standards for pre-operative planning and templating in arthroplasty. BOA guidance documents (ongoing).
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.